Dementia is becoming one of the most pressing challenges facing aging societies, particularly across Asia‑Pacific, where rapid demographic change is driving a sharp rise in prevalence. As life expectancy increases, more families are being confronted with the long‑term medical, financial and caregiving demands associated with progressive cognitive decline. Yet insurance solutions have struggled to keep pace, often reflecting models built for acute illness rather than conditions that unfold over many years.
This article examines how dementia progresses and affects longevity and the growing gap between real‑world dementia costs and insurance solutions typically available today. It also explores the implications for insurers in APAC as emerging treatments, caregiver burdens and sustainability considerations continue to challenge a large proportion of the population without suitable insurance protection.
Is dementia a normal part of aging?
Dementia is a pathological condition, distinct from normal cognitive aging. It results from abnormal changes in the brain – such as abnormal protein buildup or damaged blood vessels – that progressively impair memory, reasoning and daily functioning. Alzheimer’s disease, the most common cause of dementia, predominantly affects individuals over the age of 65, but dementia is not confined to the elderly.
Unlike age-related forgetfulness, cognitive decline in dementia is often severe enough to interfere with daily life. Over time, it leads to increasing dependency and ultimately total loss of autonomy.
How serious is the dementia challenge?
The global total caseload of Alzheimer’s disease is projected to rise from approximately 57 million in 2019 to roughly 153 million in 2050. While the age-standardized prevalence rates (ASPR) of dementia have been stabilizing or even declining in some high-income countries, the total burden of dementia continues to increase due to population aging – a greater number of people living into older, high-risk age groups. See Figure 1 below.
Estimated trends in the global age-standardised dementia prevalence and all-age number of cases, with 95% uncertainty intervals, 2019–50
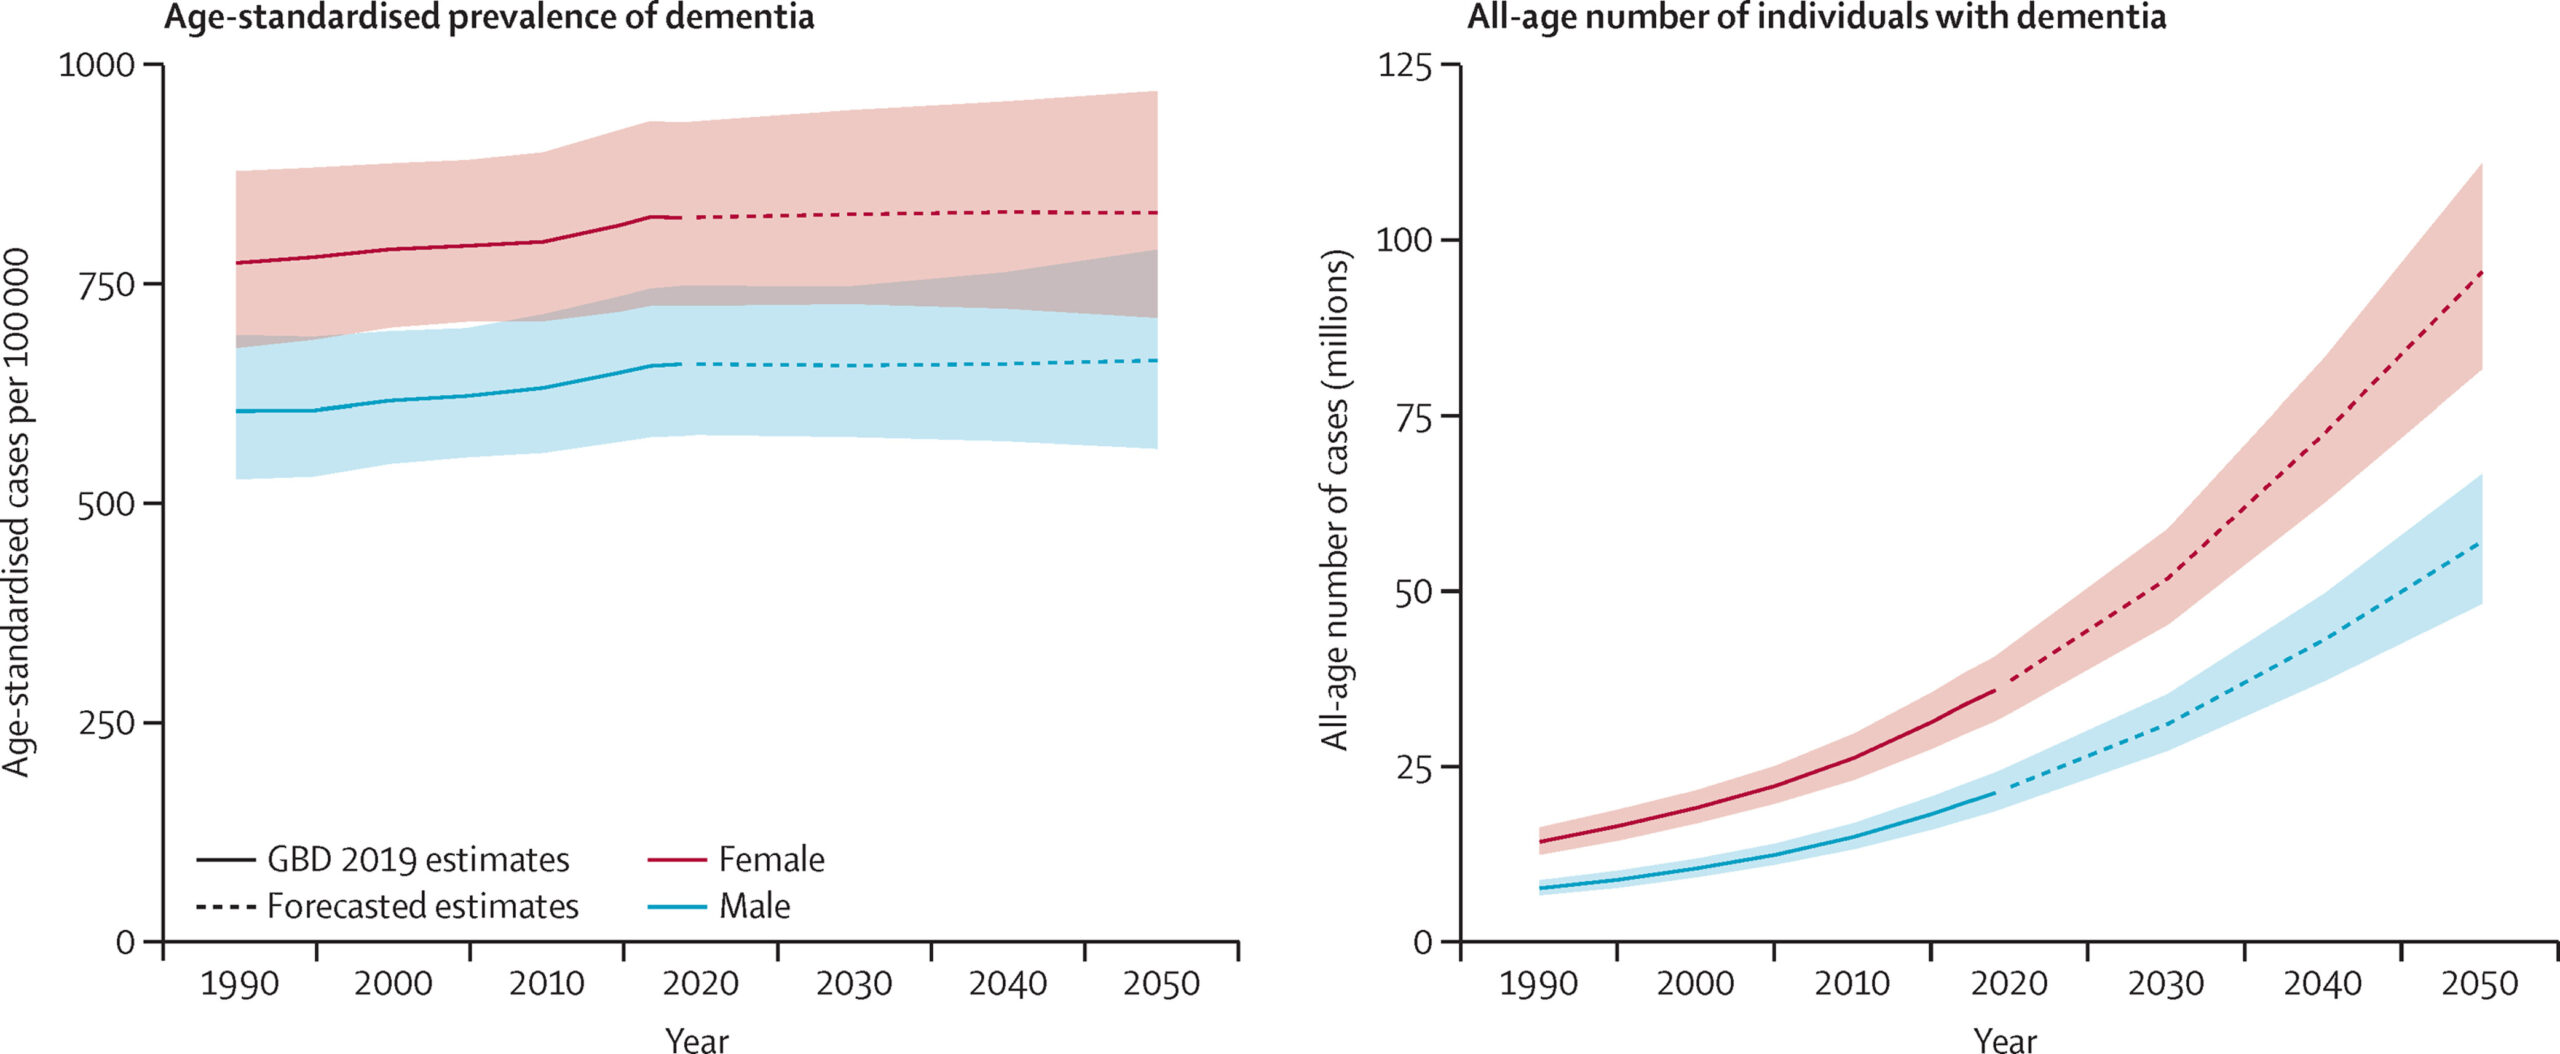
Figure 1: “Estimation of the global prevalence of dementia in 2019 and forecasted prevalence in 2050: an analysis for the Global Burden of Disease Study 2019”, Nichols E, Steinmetz J, Vollset S et al. Source: The Lancet Public Health. https://www.thelancet.com/journals/lanpub/article/PIIS2468-2667%2821%2900249-8/fulltext
The problem of population aging is particularly acute in APAC as the region is experiencing faster aging than many other parts of the world. Singapore is approaching “super-aged” status (20%+ population over 65) soon, while Japan and Korea have already crossed the threshold.
The challenge is compounded by several countries in East Asia, notably China, continuing to experience rising ASPR.[1] Projections indicate that the number of people living with dementia in APAC will triple between 2015 and 2050, growing from 23 million to almost 71 million. By then, almost half of the total number of people with dementia worldwide will reside in the APAC region.[2]
Understanding the progression of dementia
Dementia is a progressive and ultimately terminal condition, but its trajectory unfolds over time. The level of impairment, and associated financial impact, varies significantly by stage:
- Mild Cognitive Impairment (MCI): A transitional stage between normal state and mild dementia, marked by noticeable cognitive difficulties that do not yet severely disrupt independence and the disability may still be reversible.
- Mild Dementia: An early stage of decline; individuals are largely independent but experience occasional lapses in memory and judgement.
- Moderate Dementia: Cognitive impairment gradually becomes pronounced, requiring assistance with most daily tasks, but not reaching the point of total dependency.
- Severe Dementia: Accelerated loss of memory, reasoning, and ability to perform daily tasks, leading to loss of the ability to perform basic Activities of Daily Living (ADLs); individuals are likely institutionalized by this stage.
Once dementia develops, the progress is an inexorable path to total loss of independence. It is profoundly devastating – not only for patients, but also for those who care for them.
Impact on mortality and life expectancy
Dementia is considered a terminal illness that significantly reduces life expectancy. It is the 7th leading cause of death globally and a top driver of disability.[3]
Prognosis varies by dementia type:
- Alzheimer’s Disease (60-80% of cases): Characterized by a steady, progressive cognitive decline and typically the longest life expectancy. Life expectancy is often 8-10 years after diagnosis but may be up to 20 years in some cases.
- Vascular Dementia (5-10% of cases): Progresses in a stepwise manner, with sudden cognitive deterioration linked to cardiovascular risk factors. Life expectancy is generally shorter.
- Dementia with Lewy Bodies (~10% of cases): Typically progresses more rapidly than Alzheimer’s disease and may involve fluctuating cognition and motor symptoms.
- Frontotemporal Dementia (5-10% of cases): Often affects younger individuals (ages 45-65) and presents with personality, behaviour, or language changes. Life expectancy is often shorter than in Alzheimer’s disease.
Treatment: affordable care – until it isn’t
Conventional dementia treatments, such as cholinesterase inhibitors (e.g. donepezil) and NMDA receptor antagonists (e.g. memantine), can temporarily improve memory and thinking. Non-pharmacological interventions – including memory training and other ancillary, day-care services, also play a valuable role and are often subsidized by public health systems. These approaches, however, do not alter the course of disease progression.
Most recently, novel therapies such as lecanemab and donanemab have been approved to slow the progression of early Alzheimer’s by removing amyloid plaques. While clinically promising, these treatments are extremely costly and often not covered by regular medical plans.
For example, the annual drug cost of lecanemab can reach approximately USD 26,500.[4] Drug cost in Asia may be lower due to marketing factors, but the associated expenses of diagnostic imaging, monitoring and specialist consultations are still formidable.
The dementia protection gap
The rapid rise in dementia prevalence has exposed a glaring protection gap – one that goes beyond product mismatch – posing a strategic risk for insurers seeking relevance in their aging customer base.
What public systems leave behind
Japan & Korea: Both countries provide community-based dementia support, including early detection programmes, caregiver networks, and regional support centres. Yet gaps still exist. Both have national long-term care insurance requiring co-payments of 10-20% – a notable out-of-pocket cost for families. Beyond co-payments, capacity is a critical issue: in Korea alone, over 3,700 elderly applicants died in 2023 while waiting for long-term care eligibility assessment.[5]
Singapore: Community support includes dementia day care centres, outreach teams and caregiver support. However, CareShield Life — the national severe disability scheme — requires inability to perform at least 3 out of 6 ADLs to trigger payouts. Dementia alone does not automatically qualify; a functional assessment is still required, even as cognitive function declines.
Hong Kong: According to Alzheimer’s Disease International and Global Coalition on Aging, Hong Kong ranked 22nd out of 30 cities, behind Tokyo (7th) and Seoul (11th) and Singapore (16th) in terms of dementia innovation readiness.[6] The city has no national insurance scheme, and the waiting time for screening diagnosis in subsidised public hospitals can be over a year.
Where public systems fall short, the burden shifts to families and to the private sector. But is private insurance sufficient?
When help comes too late
Standard private critical illness plans were designed around conditions where a defined event triggers a clear need for intervention or income replacement. Dementia does not fit this mould. It is protracted, degenerative, and financially draining, years before clinical severity triggers a payout.
Families face significant costs during the moderate stage – supervision, medication, lost income. Yet many policies still define coverage around late-stage dependency requiring round-the-clock care, by which point savings may be exhausted. While some plans already cover moderate dementia, the broader challenge remains; dementia is a long, slow decline. A single lump sum, however well-timed, may not align with years of accumulating expenses. In Singapore, for example, lifetime dementia-related costs for a 10-year survivor can reach SGD 1.6 million.[7] Delaying protection benefits until total dependency eventuates leaves families stranded during the most financially vulnerable years.
The silent second victim
For every dementia patient, at least one family member typically assumes a caregiving role. If 10% of the population is affected by dementia, another 10-20% bear the associated caretaking burden. The consequences — emotional strain, lost productivity and depleted savings — extend the impact of dementia to nearly one in three people. Ignoring caregivers means overlooking the full scale of the risk.
Challenges and opportunities for the re/insurance industry
With the population aging inexorably, demand for dementia-related support will only grow and insurance protection can play an important role. Nonetheless, insurers have a challenging path to navigate as they pursue this opportunity.
The realities of the risk
Dementia is uniquely difficult to insure. Most critically, the condition is highly susceptible to anti-selection. Biomarkers can appear years before MCI is clinically detectable, and genetic tests can indicate elevated risk well in advance. Furthermore, the duration from MCI to moderate dementia can be very long – sometimes a decade or more – giving individuals who suspect they are at risk of developing dementia or already earlier onset, ample time to seek coverage. This makes traditional risk selection exceptionally challenging.
Beyond anti-selection, there is a more fundamental question: what is the right benefit design? Monetary support would be most meaningful at the earlier stages of the disease, where emerging drug therapies offer the greatest clinical value. However, providing significant benefits at early stages is challenging due to higher risk of anti-selection and difficulty in traditional risk assessment. A standard critical illness payout, designed for acute events, may be ill-suited to a condition that demands sustained support — covering both early treatment access and ongoing non-clinical needs like home modifications and care coordination. Designing alternative benefit structures that balance meaningful support with manageable risk remains an unresolved challenge for the industry.
Reframing the opportunity
The very challenges of dementia — its long-tail nature, uncertain trajectory, and mismatch with traditional insurance models — opens a different kind of opportunity. For insurers willing to engage, this is a chance to raise awareness of the condition’s true impact and develop tailored products for an underserved risk. Because dementia emerges later in life, meaningful protection must be purchased well before onset. This is not merely about targeting a niche elderly segment, but also about helping a broader customer base to understand the value of planning ahead.
Directions worth exploring
- Rethinking benefit structures: A lump sum alone may not be the right answer. Alternative designs — such as smaller payments triggered by the use of specific care services (e.g., home modifications, day programmes) — could better align with the real, ongoing needs of patients and families.
- Supporting early intervention: Based on current clinical evidence, new therapies appear most effective in the earliest stages of dementia. Products that facilitate access to timely diagnosis and treatment — rather than waiting for severe disability — could improve patient outcomes, though the long-term trajectory of medical advancement remains uncertain.
- Extending coverage to caregivers: A few insurers now recognize that protecting the caregiver’s own wellbeing — with benefits that fund respite care, counselling or mental health support – is essential to sustaining the patient’s care ecosystem – and that doing so differentiates their offering in a crowded market.
- Encouraging earlier purchase: True sustainability requires engaging customers earlier in life, when premiums are affordable and risk is not yet present. This is as much about consumer education as product design.
None of these options are easy to execute but for insurers willing to work through the complexities, dementia represents a growing area of customer need that the industry has only begun to address.
Contact Us
PartnerRe works closely with insurers to navigate these challenges, combining medical insight, underwriting expertise and regional market experience to support the development of sustainable dementia solutions. Contact us to discuss how we can help you respond to the changing needs of aging populations.
Contributors
Dr. Peter Lau, Chief Medical Officer, Asia Pacific
Bernice Yu, Senior Director, Product & Solutions – Greater China and Southeast Asia, Life & Health
This article is for general information, education and discussion purposes only and does not in any way constitute medical, legal or professional advice.
References
[1] “The current status, trends, and challenges of Alzheimer’s disease and other dementias in Asia (1990–2036)”. | Frontiers
[2] “Dementia in the Asia Pacific Region” | Alzheimer’s Disease International (ADI)
[3] “The top 10 causes of death”, World Health Organization, August 7, 2024.
[4] “Eisai’s Approach to U.S. Pricing for Leqembi™ (lecanemab)”, Eisai Global, January 7, 2023.
[5] “대기 중 사망자 3700명… 노인 요양보험, 뭐가 문제일까?”
[6] “Dementia Innovation Readiness Index 2020”, Alzheimer’s Disease International, Global Coalition on Aging and Lien Foundation.
[7] “The true cost of dementia: It can set a family back by up to $1.6m over 10 years”, The Strait Times, March 31, 2025.
Dementia is becoming one of the most pressing challenges facing Canada’s aging society, driving a sharp rise in prevalence and placing growing strain on families, public systems, and the insurance industry. As life expectancy increases, more Canadians are confronting the long-term medical, financial, and caregiving demands of progressive cognitive decline — yet insurance solutions have struggled to keep pace.
This article examines how dementia progresses and affects longevity, the growing gap between real-world dementia costs and available insurance solutions in Canada, and the implications for insurers as emerging treatments, caregiver burdens, and sustainability considerations continue to challenge a large proportion of the population without suitable protection.
Is dementia a normal part of aging?
Dementia is a pathological condition, distinct from normal cognitive aging. It results from abnormal changes in the brain — such as abnormal protein buildup or damaged blood vessels — that progressively impair memory, reasoning, and daily functioning. Alzheimer’s disease, the most common cause of dementia, predominantly affects individuals over the age of 65, but dementia is not confined to the elderly.[1]
Unlike age-related forgetfulness, cognitive decline in dementia is often severe enough to interfere with daily life. Over time, it leads to increasing dependency and ultimately total loss of autonomy.
How serious is the dementia challenge in Canada?
Globally, the total caseload of dementia is projected to rise from approximately 57 million in 2021 to roughly 153 million by 2050.[2] While age-standardized prevalence rates have been stabilizing or are even declining in some high-income countries — including Canada — the total burden continues to increase due to population aging – a greater number of people living into older, high-risk age groups. See Figure 1 below.
Estimated trends in the global age-standardised dementia prevalence and all-age number of cases, with 95% uncertainty intervals, 2019–50
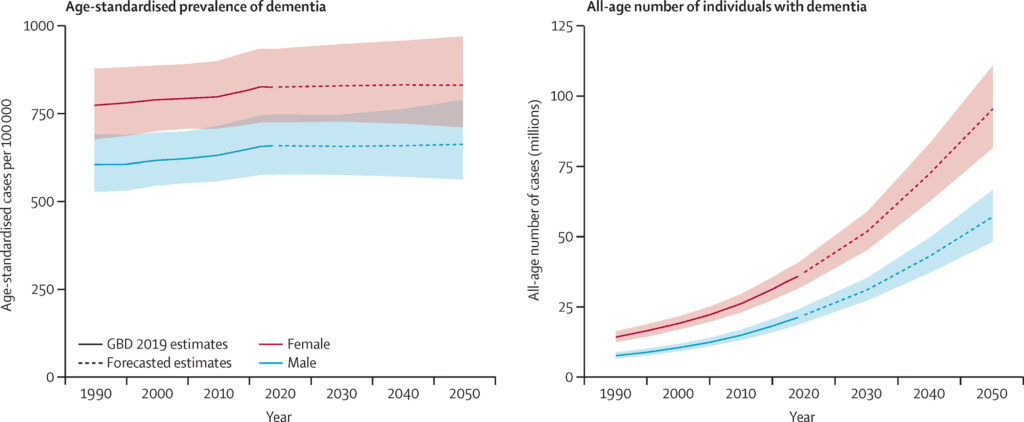
Figure 1: “Estimation of the global prevalence of dementia in 2019 and forecasted prevalence in 2050: an analysis for the Global Burden of Disease Study 2019”, Nichols E, Steinmetz J, Vollset S et al. Source: The Lancet Public Health. https://www.thelancet.com/journals/lanpub/article/PIIS2468-2667%2821%2900249-8/fulltext
Canada faces a particularly acute challenge:
- Approximately 772,000 Canadians were living with dementia as of early 2025 with projections of nearly 1 million by 2030 and more than 1.7 million by 2050.[3] [4]
- In Ontario, community dementia prevalence increased 9.5% (2010–2015) even as age-specific incidence fell 15.8% — a paradox driven by longer post-diagnosis survival and population aging.[5]
- Canada’s population aged 65+ is projected to rise substantially, reaching about 9 to 10.9 million by 2036 and 11.9 to 15.0 million by 2061, or roughly 23% to 28% of the population.[6]
- Young-onset dementia (before age 65) prevalence in Ontario has tripled between 1996 and 2016 (from 0.11 to 0.32 per 100 population).[7] Globally, young-onset dementia prevalence is estimated at 119 per 100,000.[8]
Understanding the progression of Dementia
Dementia is a progressive and ultimately terminal condition, but its trajectory unfolds over time. The level of impairment, and associated financial impact, varies significantly by stage:
- Mild Cognitive Impairment (MCI): A transitional stage between normal cognition and mild dementia, marked by noticeable cognitive difficulties that do not yet severely disrupt independence. The disability may still be reversible.
- Mild Dementia: An early stage of decline; individuals are largely independent but experience occasional lapses in memory and judgement.
- Moderate Dementia: Cognitive impairment gradually becomes pronounced, requiring assistance with most daily tasks, but not reaching the point of total dependency.
- Severe Dementia: Accelerated loss of memory, reasoning, and ability to perform daily tasks, leading to loss of the ability to perform basic Activities of Daily Living (ADLs); individuals are likely institutionalized by this stage.
Once dementia develops, progress is an inexorable path to total loss of independence. It is profoundly devastating not only for patients, but also for those who care for them.
Impact on mortality and life expectancy
Dementia is considered a terminal illness that significantly reduces life expectancy. It is the 7th leading cause of death globally and a top driver of disability.[9] Critically, dementia is underreported on approximately 25% of death certificates, meaning vital statistics substantially underestimate its true contribution to mortality.[10]
In Canada, the evidence is stark. The Canadian Study of Health and Aging found a median survival of 6.6 years from symptom onset— reduced to 3.3 years after adjustment for length bias, reflecting that many cases are diagnosed well after onset[11] In Ontario (N=108,757), 55% of patients died within 5 years of diagnosis, with five-year mortality ranging from 22% to 91% depending on age, sex, and comorbidities.[12] Those diagnosed before age 65 lose an estimated 15 years of potential life.[13]
Prognosis varies by dementia type:
- Alzheimer’s Disease (60–80% of cases, including mixed AD/vascular): Characterized by steady, progressive cognitive decline and typically the longest survival. Life expectancy is often 8–10 years after diagnosis but may be up to 20 years in some cases.[14]
- Vascular Dementia (10-20% of cases): Progresses in a stepwise manner, with sudden cognitive deterioration linked to cardiovascular risk factors. Life expectancy is generally shorter.[15]
- Dementia with Lewy Bodies (~4–6% of cases): Typically progresses more rapidly than Alzheimer’s disease and may involve fluctuating cognition and motor symptoms.[16]
- Frontotemporal Dementia (1–8% of cases): Often affects younger individuals (ages 45–65) and presents with personality, behavior, or language changes. Life expectancy is often shorter than in Alzheimer’s disease.[17]
Modifiable risk factors — a Canadian perspective
Analysis of 30,097 Canadians from the Canadian Longitudinal Study on Aging (CLSA) found that 12 modifiable risk factors account for an estimated 43–61% of dementia cases in Canada. The top contributors by weighted population attributable fraction: physical inactivity (11.6%), depression (7.7%), and hypertension (6.0%). The study findings also indicated socioeconomic differences, where 9 of 12 factors were observed to be more prevalent among lower income groups, suggesting that social determinants may influence dementia risk.[18]
The diabetes–dementia connection
One of the most significant modifiable risk factors is type 2 diabetes mellitus (T2DM), which increases Alzheimer’s disease risk by 36–53% and vascular dementia risk by approximately 2.3x.[19] Earlier diabetes onset amplifies risk further — each 5-year younger age at diabetes onset increases dementia hazard by approximately 24%.[20] Researchers have termed Alzheimer’s disease “Type 3 Diabetes” to reflect the brain’s own form of insulin resistance that drives neurodegeneration.[21] This is not a formal diagnostic category but a powerful framework linking two of the world’s largest chronic disease burdens through shared metabolic pathology as explored in an earlier PartnerRe publication. For insurers, this means that comprehensive cardiometabolic risk management — glycemic control, cardiovascular health, weight management, physical activity — is simultaneously dementia prevention: a dual value proposition.
Treatment: affordable care — until it isn’t
Conventional dementia treatments, such as cholinesterase inhibitors (e.g., donepezil) and NMDA receptor antagonists (e.g., memantine), can temporarily improve memory and thinking. Non-pharmacological interventions — including memory training and other ancillary, day-care services — also play a valuable role. In Canada, all provincial public drug plans provide coverage for cholinesterase inhibitors for mild-to-moderate dementia, although coverage criteria and administration requirements vary widely by province. These approaches, however, do not alter the course of disease progression.
Novel disease-modifying therapies such as lecanemab and donanemab have been approved in some jurisdictions to slow the progression of early Alzheimer’s by removing amyloid- β plaques. While clinically promising, these treatments are extremely costly.[22] Canada does not yet have the diagnostic, treatment, and monitoring infrastructure required for widespread use of disease-modifying therapies, and their introduction may strain an already resource-constrained healthcare system.[23]
Notably, despite strong preclinical promise, GLP-1 receptor agonists (e.g., semaglutide, liraglutide) have not demonstrated cognitive benefit in prospective clinical trials to date.[24] [25] [26]
The dementia protection gap in Canada
The rapid rise in dementia prevalence has exposed a significant protection gap — one that goes beyond product mismatch, posing a strategic risk for insurers seeking relevance in their aging customer base.
What Canada’s public system leaves behind
Canada’s universal healthcare system covers physician and hospital services for all Canadians, providing a strong foundation[27]. However, dementia care extends far beyond what the public system covers:
- Long-term care: Provincially administered with significant co-payments and long wait lists. Canada faces a shortfall of approximately 15,000 long-term care beds today, projected to reach 157,000 by 2038.[28] In Ontario, 49% of people with dementia spent time in long-term care within 7 years of diagnosis[29].
- Home care: Covered partially but varies widely by province. Persons with dementia use home care at 3× the rate of those without, and this rate grows by ~11% per year as they remain in the community[30].
- Prescription drugs: Coverage is a patchwork — some provinces cover all seniors (e.g., Ontario), while others are income-tested (e.g., British Columbia). Approximately 25–33% of Canadians lack supplemental insurance for outpatient medications[31].
- Novel therapies: Disease-modifying treatments like lecanemab are unlikely to be covered by provincial plans in the near term, leaving families to bear costs privately.
Where the public system falls short, the burden shifts to families and to the private sector.
When help comes too late
Standard private critical illness plans were designed around conditions where a defined event triggers a clear need for intervention or income replacement. Dementia does not fit this mould as neatly. It is protracted, degenerative, and can create financial pressure years before clinical severity triggers a payout.
Families may face significant costs during the moderate stage — supervision, medication, lost income. Yet many policies still define coverage around late-stage dependency, by which point savings may already be meaningfully depleted. US research demonstrates that individual wealth drops by nearly two-thirds within 8 years of dementia diagnosis[32] — a pattern that may have relevance in Canada as well. The total economic burden of dementia in Canada — including direct healthcare and informal caregiving costs — is estimated at ~$15 billion/year nationally, projected to reach $153 billion per year by 2038[33]. When protection benefits are available only at the point of total dependency, families may receive support after the period when financial pressure has already become acute.
The silent second victim
For every dementia patient, at least one family member typically assumes a caregiving role. In Canada, 85% of persons with dementia in private households rely at least in part on family, friends, or neighbors for care. The primary caregiver is typically a spouse (46%) or adult child (44%), most of whom are daughters (71%). The majority live in the same household (83%) and provide daily care (86%)[34].Caregivers of patients with moderate and severe AD have increased comorbidities (hypertension, depression/anxiety, insomnia), require more medication and physician visits — and incur significant excess healthcare costs, compared to non-caregivers[35]. Ignoring caregivers means overlooking the full scale of the risk.
Challenges and opportunities for the re/insurance industry
With Canada’s population aging inexorably, demand for dementia-related support will only grow and insurance protection can play an important role. Nonetheless, insurers have a challenging path to navigate.
The realities of the risk
Dementia is uniquely difficult to insure. Most critically, the condition is highly susceptible to anti-selection. Blood biomarkers (e.g., plasma p-tau217) can now indicate Alzheimer’s underlying pathology (not the certainty of future clinical dementia) many years before clinical symptoms[36], and genetic tests can indicate elevated risk well in advance. Canada’s Genetic Non-Discrimination Act (GNDA) prohibits insurers from requiring genetic testing and restricts insurers from using genetic test results for underwriting purposes— a protection that does not exist in most other jurisdictions[37]. While the GNDA protects consumers, it also makes it very difficult for Canadian insurers to use predictive genetic information (e.g., APOE ε4 status) for risk selection, potentially increasing exposure to adverse selection as genetic and biomarker testing becomes more accessible.
Beyond anti-selection, there is a more fundamental question: what is the right benefit design? Monetary support would be most meaningful at the earlier stages of the disease, where emerging drug therapies may offer the greatest clinical value. However, providing significant benefits at early stages is challenging due to higher risk of anti-selection and difficulty in traditional risk assessment. A standard critical illness payout, designed for acute events, may be ill-suited to a condition that demands sustained support — covering both early treatment access and ongoing non-clinical needs like home modifications and care coordination. Designing alternative benefit structures that balance meaningful support with manageable risk remains an unresolved challenge for the industry.
Reframing the opportunity
The very challenges of dementia, from its long-tail nature, uncertain trajectory, and mismatch with traditional insurance models, open a different kind of opportunity. For insurers willing to engage, this is a chance to raise awareness of the condition’s true impact and develop tailored products for an underserved risk. Because dementia emerges later in life, meaningful protection must be purchased well before onset. This is not merely about targeting a niche elderly segment but about helping a broader customer base understand the value of planning ahead.
Directions worth exploring
- Rethinking benefit structures: There may be alternative designs (beyond single lump sum payment) worth considering — such as smaller phased payments triggered by the use of specific care services (e.g., home modifications, day programmes). These benefit structures could in theory better align with the real, ongoing needs of patients and families.
- Supporting early intervention: Based on current clinical evidence, new therapies appear most effective in the earliest stages of dementia. Products that facilitate access to timely diagnosis and treatment — rather than waiting for severe disability — could improve patient outcomes, though the long-term trajectory of medical advancement remains uncertain.
- Extending coverage to caregivers: Recognizing that protecting the caregiver’s own wellbeing — with benefits that fund respite care, counselling, or mental health support — is essential to sustaining the patient’s care ecosystem and differentiating offerings in a crowded market.
- Leveraging the diabetes–dementia link: Integrated wellness programs that address cardiometabolic risk factors (glycemic control, blood pressure, physical activity) simultaneously reduce dementia risk — a dual value proposition that strengthens the case for proactive health management and earlier customer engagement.
- Encouraging earlier purchase: True sustainability requires engaging customers earlier in life, when premiums are affordable and risk is not yet present. This is as much about consumer education as product design.
None of these options are easy to execute, and pricing can be a challenge given inherent uncertainties, but for insurers willing to work through the complexities, dementia represents a growing area of customer need that the industry has only begun to address.
Contact Us
PartnerRe works closely with insurers to navigate these challenges, combining medical insight, underwriting expertise and regional market experience to support the development of sustainable product solutions. Contact us to learn more.
Contributors:
Dr. Peter Lau, Chief Medical Officer, Asia Pacific and Bernice Yu, Senior Director, Product & Solutions – Greater China and Southeast Asia, Life & Health authored the original article. Link: Dementia: The Protection Gap Insurers Can No Longer Ignore | PartnerRe
Dr. Emoke Posan MD, PhD. Chief Medical Officer, Life, North America – adapted and expanded the content with Canadian-specific context.
Opinions expressed herein are solely those of the authors. This article is for general information, education, and discussion purposes only. It does not in any way constitute medical, legal or professional advice and does not necessarily reflect, in whole or in part, any corporate position, opinion or view of PartnerRe or its affiliates.
References
[1] Falk N, Cole A, Meredith TJ. “Evaluation of Suspected Dementia.” American Family Physician. 2018;97(6):398-405.
[2] Nichols E, Steinmetz J, Vollset S, et al. “Estimation of the global prevalence of dementia in 2019 and forecasted prevalence in 2050: an analysis for the Global Burden of Disease Study 2019.” The Lancet Public Health. 2022;7(2):e105-e125.
[3] Feldman HH, Estabrooks CA. “The Canadian Dementia Challenge: Ensuring Optimal Care and Services for Those at Risk or With Dementia Throughout the Country.” Canadian Journal of Public Health. 2017;108(1):e95-e98.
[4] Alzheimer Society of Canada. The Landmark Study: Report 1. Toronto, ON: Alzheimer Society of Canada; 2022.
[5] Vanderkruk KR, Eberg M, Mahootchi T,et al. Trends of Dementia among Community-Dwelling Adults in Ontario, Canada, 2010-2015. Dement Geriatr Cogn Disord. 2020;49(3):286-294. doi: 10.1159/000508687.
[6] Statistics Canada. Population Projections for Canada, Provinces and Territories. 2024.
[7] Jaakkimainen L, Duchen R, Lix L, et al. “Identification of Early Onset Dementia in Population-Based Health Administrative Data: A Validation Study Using Primary Care Electronic Medical Records.” Journal of Alzheimer’s Disease. 2022;86(4):1731-1742.
[8] Hendriks S, Peetoom K, Bakker C, et al. “Global Prevalence of Young-Onset Dementia: A Systematic Review and Meta-analysis.” JAMA Neurology. 2021;78(9):1080-1090.
[9] World Health Organization. “The top 10 causes of death.” August 7, 2024
[10] Stokes AC, Weiss J, Lundberg DJ, et al. “Estimates of the Association of Dementia With US Mortality Levels Using Linked Survey and Mortality Records.” JAMA Neurology. 2020;77(12):1543-1550.
[11] Wolfson C, Wolfson DB, Asgharian M, et al. “A Reevaluation of the Duration of Survival after the Onset of Dementia.” NEJM. 2001;344:1111-1116.
[12] Huyer G, Brown CRL, Spruin S, et al. “Five-Year Risk of Admission to Long-Term Care Home and Death for Older Adults Given a New Diagnosis of Dementia: A Population-Based Retrospective Cohort Study.” CMAJ. 2020;192(16):E422-E430.
[13] Lichtenstein ML, et al. 16-Year Survival of the Canadian Collaborative Cohort of Related Dementias. Canadian Journal of Neurological Sciences. 2018;45(6):660-667.
[14] Falk N, Cole A, Meredith TJ. “Evaluation of Suspected Dementia.” American Family Physician. 2018;97(6):398-405.
[15] Lichtenstein ML, et al. 16-Year Survival of the Canadian Collaborative Cohort of Related Dementias. Canadian Journal of Neurological Sciences. 2018;45(6):660-667.
[16] Arvanitakis Z, Shah RC, Bennett DA. “Diagnosis and Management of Dementia: Review.” JAMA. 2019;322(16):1589-1599.
[17] Falk N, Cole A, Meredith TJ. “Evaluation of Suspected Dementia.” American Family Physician. 2018;97(6):398-405.
[18] Dolatshahi Y, Mayhew A, O’Connell ME, et al. “Prevalence and Population Attributable Fractions of Potentially Modifiable Risk Factors for Dementia in Canada: A Cross-Sectional Analysis of the Canadian Longitudinal Study on Aging.” Canadian Journal of Public Health. 2024.
[19] Gudala K, Bansal D, Schifano F, Bhansali A. “Diabetes mellitus and risk of dementia: A meta-analysis of prospective observational studies.” Journal of Diabetes Investigation. 2013;4(6):640-650.
[20] Barbiellini Amidei C, Fayosse A, Dumurgier J, et al. “Association Between Age at Diabetes Onset and Subsequent Risk of Dementia.” JAMA. 2021;325(16):1640-1649.
[21] de la Monte SM, Wands JR. “Alzheimer’s disease is type 3 diabetes — evidence reviewed.” Journal of Diabetes Science and Technology. 2008;2(6):1101-1113.
[22] Eisai’s Approach to U.S. Pricing for Leqembi™ (lecanemab)”, Eisai Global, January 7, 2023. https://www.eisai.com/news/2023/news202302.html
[23] Frank A, Ismail Z, Wilson M, et al. “Health System Change for Alzheimer’s Disease-Modifying Therapies in Canada: Beginning the Discussion.” Canadian Journal of Neurological Sciences. 2023.
[24] Edison P, Femminella GD, Ritchie CW, et al. “Evaluation of Liraglutide in the Treatment of Alzheimer’s Disease (ELAD): A Randomised Phase IIb Trial.” The Lancet. 2023.
[25] Cukierman-Yaffe T, Gerstein HC, Colhoun HM, et al. “Effect of dulaglutide on cognitive impairment in type 2 diabetes: an exploratory analysis of the REWIND trial.” The Lancet Neurology. 2020;19(7):582-590.
[26] Cummings JL, Atri A, Sano M, et al. “Efficacy and Safety of Oral Semaglutide 14 mg in Early-Stage Symptomatic Alzheimer’s Disease (EVOKE and EVOKE+): Two Phase 3, Randomised, Placebo-Controlled Trials.” The Lancet. 2026.
[27] Martin D, Miller AP, Quesnel-Vallée A, et al. “Canada’s Universal Health-Care System: Achieving Its Potential.” The Lancet. 2018;391(10131):1718-1735.
[28] Rockwood K, Keren R. “Dementia services in Canada.” International Journal of Geriatric Psychiatry. 2010;25(9):876-880.
[29] Bronskill SE, Maclagan LC, Walker JD, et al. “Trajectories of Health System Use and Survival for Community-Dwelling Persons With Dementia: A Cohort Study.” BMJ Open. 2020;10(7):e037485.
[30] Bronskill SE, Maclagan LC, Walker JD, et al. “Trajectories of Health System Use and Survival for Community-Dwelling Persons With Dementia: A Cohort Study.” BMJ Open. 2020;10(7):e037485
[31] Martin D, Miller AP, Quesnel-Vallée A, et al. “Canada’s Universal Health-Care System: Achieving Its Potential.” The Lancet. 2018;391(10131):1718-1735.
[32] Choi H, Langa KM, Norton EC, Cho TC, Connell CM. “Changes in Care Use and Financial Status Associated With Dementia in Older Adults.” JAMA Internal Medicine. 2023;183(12):1389-1396.
[33] Rockwood K, Keren R. “Dementia services in Canada.” International Journal of Geriatric Psychiatry. 2010;25(9):876-880.
[34] Wong SL, Gilmour H, Ramage-Morin PL. “Alzheimer’s Disease and Other Dementias in Canada.” Health Reports (Statistics Canada). 2016;27(5):11-16.
[35] Szabo S, Lakzadeh P, Cline S, Palma Dos Reis R, Petrella R. “The clinical and economic burden among caregivers of patients with Alzheimer’s disease in Canada.” International Journal of Geriatric Psychiatry. 2019;34(11):1677-1688.
[36] Frisoni GB, Hansson O, Nichols E, et al. “New Landscape of the Diagnosis of Alzheimer’s Disease.” The Lancet. 2025.
[37] “Canada’s Supreme Court Upholds Law to Prevent Genetic Discrimination.” American Journal of Medical Genetics Part A. 2020;182(10):2204-2205.
